When patients walk into a physiotherapy clinic, they expect more than just a printed sheet of exercises. They expect hands-on expertise. Manual therapy remains one of the most powerful, highly requested, and clinically effective tools in a physiotherapist’s arsenal for treating musculoskeletal, neuromuscular, and sports-related conditions.
But what exactly happens when a physiotherapist places their hands on a patient?
Whether you are a patient seeking relief from chronic pain, a physiotherapy student brushing up on clinical skills, or an internationally educated physiotherapist preparing for rigorous global licensing exams, understanding the exact science and application of manual therapy is strictly non-negotiable.
In this comprehensive, evidence-based guide, we break down the "Big Three" of manual therapy: Joint Mobilisation, Joint Manipulation, and Myofascial Release (MFR). We will explore the biomechanics behind them, precise clinical indications, and critically how mastering these techniques is your absolute golden ticket to passing overseas licensing pathways like the APEP (Australia), HCPC (UK), and DHA (Dubai).
What is Manual Therapy in Physiotherapy?
At its core, physiotherapy manual therapy is a specialized clinical approach utilizing skilled, specific hands-on techniques. Unlike general massage, which primarily focuses on relaxation and blood flow, manual therapy is highly targeted and driven by meticulous clinical reasoning.
The International Federation of Orthopaedic Manipulative Physical Therapists (IFOMPT) defines it as a comprehensive approach to managing neuromusculoskeletal conditions. It is never meant to be used in isolation; the absolute best outcomes occur when manual therapy is paired with therapeutic exercise and patient education.
The Primary Goals of Manual Therapy:
- Modulate Pain: By stimulating mechanoreceptors to override nociceptive (pain) signals.
- Increase Joint Range of Motion (ROM): By stretching tight joint capsules and ligaments.
- Reduce Soft Tissue Inflammation: By improving local fluid dynamics and tissue mobility.
- Improve Tissue Repair: By facilitating proper collagen alignment during the healing phase.
- Facilitate Movement: By breaking movement dysfunctions and improving neuromuscular control.
Let's dive into the three primary pillars of this hands-on approach.
Joint Mobilisation
Joint mobilisation involves skilled, passive movements applied to joints and their related soft tissues at varying speeds and amplitudes. The defining, foundational characteristic of mobilisation is that it is performed at a speed slow enough that the patient can actively stop the movement if they feel discomfort.
Physiological vs. Accessory Movements
To understand mobilisation, you must understand how human joints articulate.
- Physiological (Osteokinematic) Movements: These are gross movements the patient can perform actively (e.g., bending the knee, lifting the arm over the head, twisting the spine).
- Accessory (Arthrokinematic) Movements: These are micro-movements occurring inside the joint capsule that the patient cannot perform actively. They consist of gliding, rolling, and spinning of the joint surfaces.
Mobilisation specifically targets restricted accessory movements. If a joint cannot glide properly, it cannot achieve full physiological range of motion.
The Convex-Concave Rule
A core tenet of joint mobilisation is the Convex-Concave rule, which dictates the direction of the mobilisation glide:
- Convex on Concave: When a convex joint surface moves on a stable concave surface, the internal glide occurs in the opposite direction of the bone movement (e.g., the shoulder joint).
- Concave on Convex: When a concave surface moves on a stable convex surface, the glide occurs in the same direction as the bone movement (e.g., the knee joint).
The Maitland Concept: Grades of Mobilisation
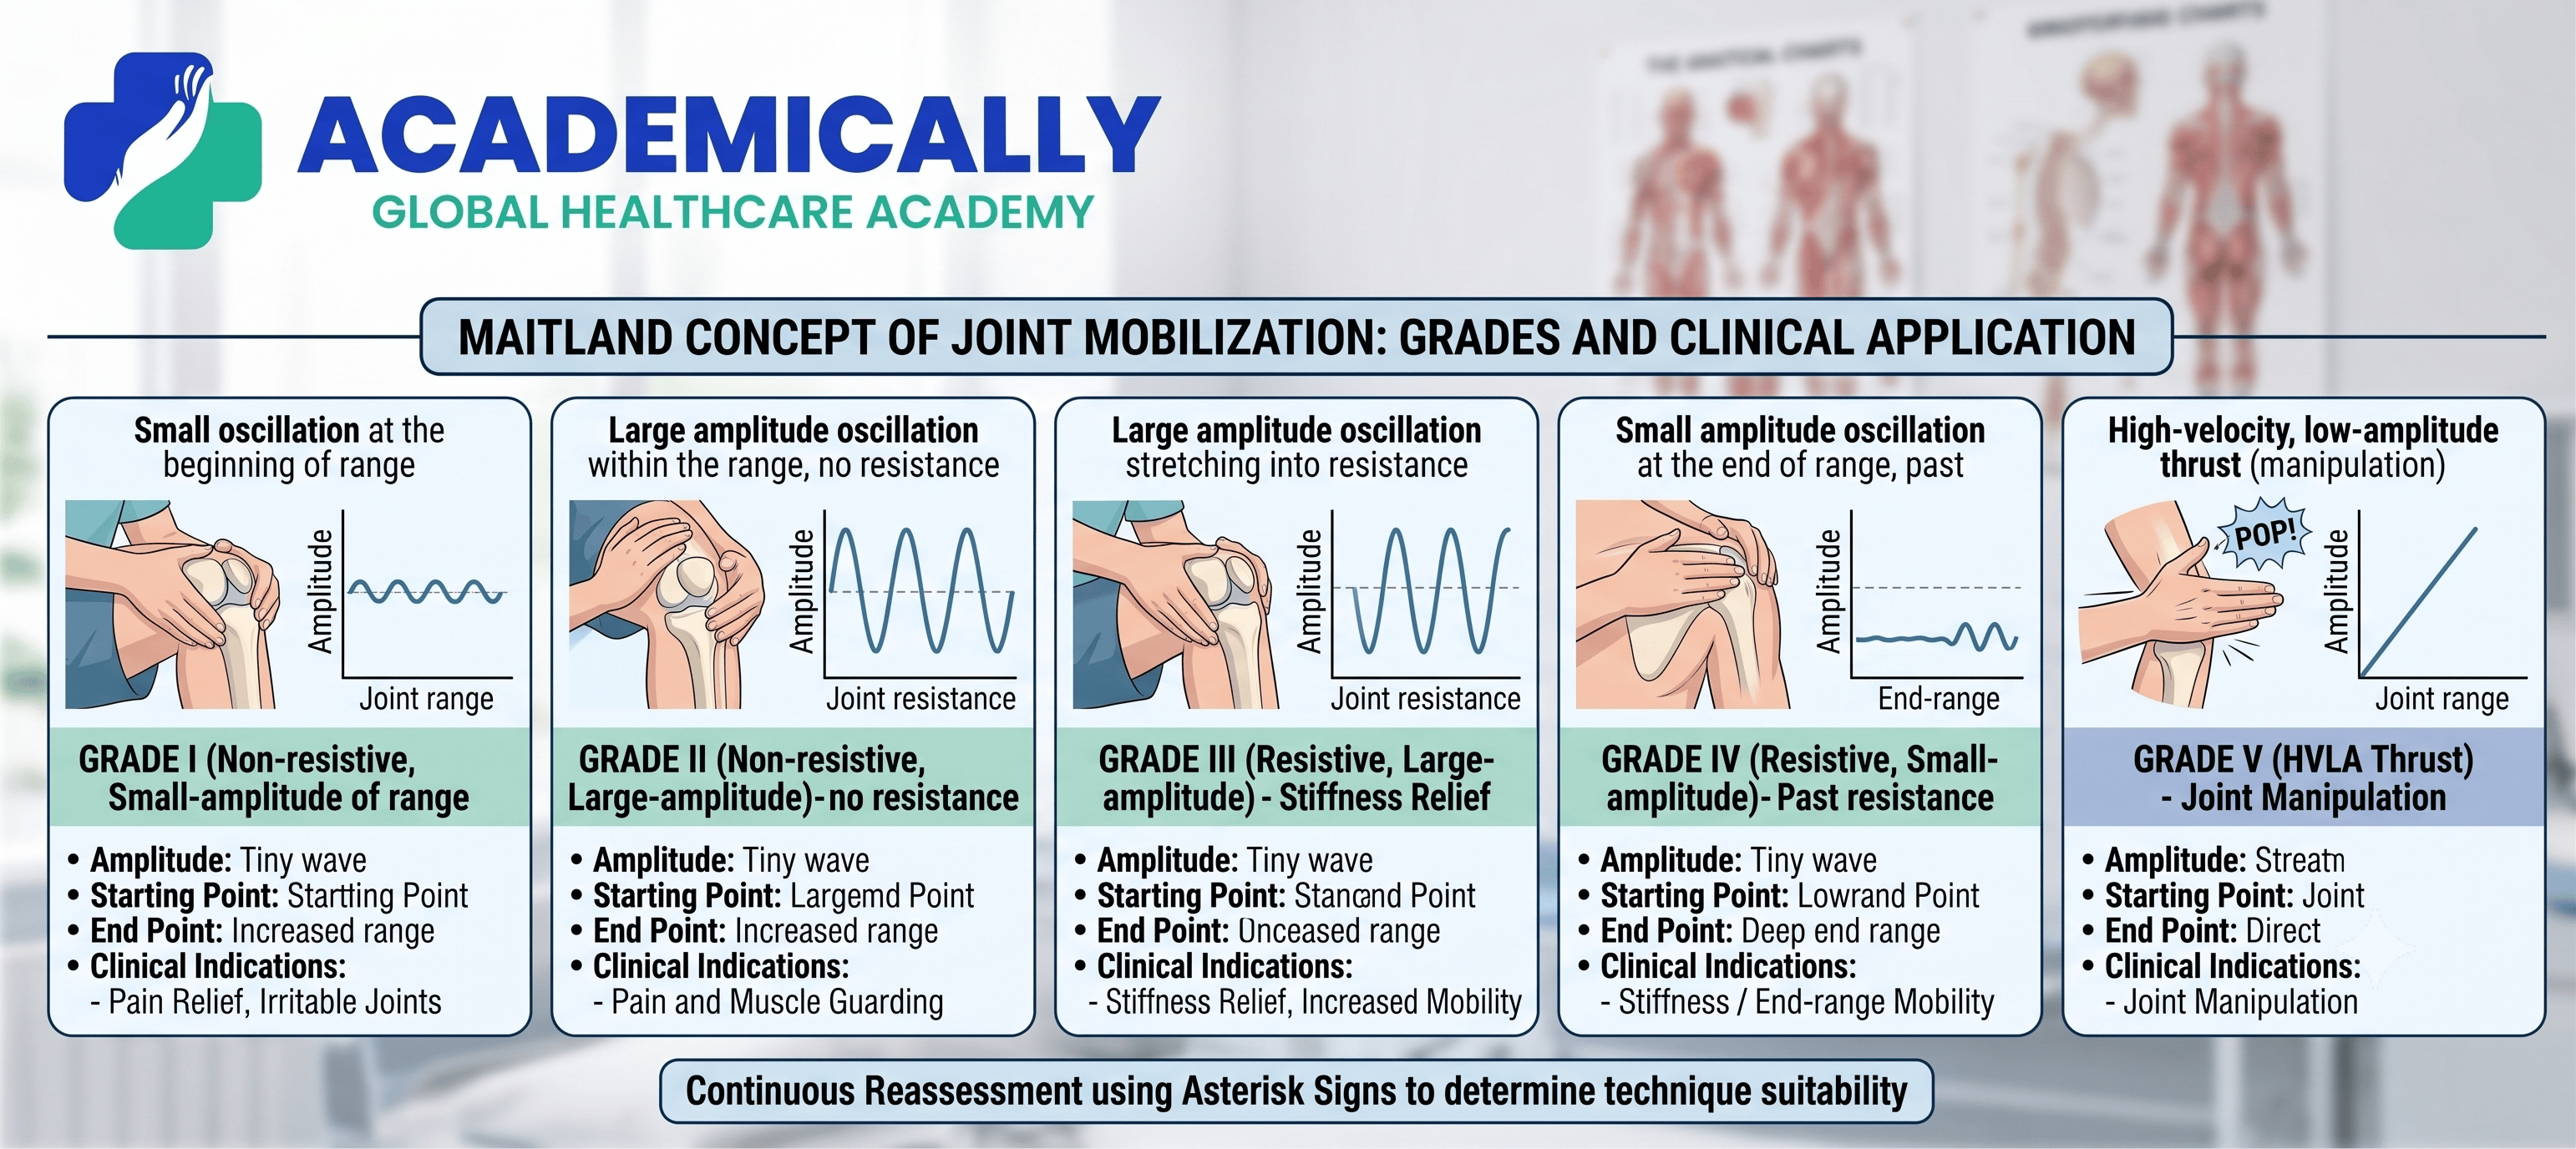
Australian physiotherapist Geoffrey Maitland pioneered a grading system that remains the global gold standard in musculoskeletal physical therapy. The grades are based on the amplitude (size) of the movement and where it falls within the joint's available range of tissue resistance.
- Grade I: A small amplitude rhythmic oscillating movement performed at the very beginning of the available range of motion. (Primary use: Pain relief in highly irritable joints).
- Grade II: A large amplitude rhythmic oscillating movement performed within the free range, not reaching the tissue limit. (Primary use: Pain relief and reducing muscle guarding).
- Grade III: A large amplitude rhythmic oscillating movement performed right up to the limit of the available range. (Primary use: Stretching the joint capsule to increase mobility).
- Grade IV: A small amplitude rhythmic oscillating movement performed at the very end of the available range, pushing into tissue resistance. (Primary use: Aggressive stretching for stiff, non-irritable joints).
- Grade V (Maitland Manipulation): A High-Velocity, Low-Amplitude (HVLA) thrust performed at the limit of the range. As indicated in image_1.png, Grade V is defined by a rapid, straight application of force ('direct') used specifically for Joint Manipulation, which often results in the audible 'pop' (cavitation). (Primary use: Rapid neurophysiological reset, immediate pain relief, and resetting muscle tone).
The Kaltenborn Approach: Sustained Glides
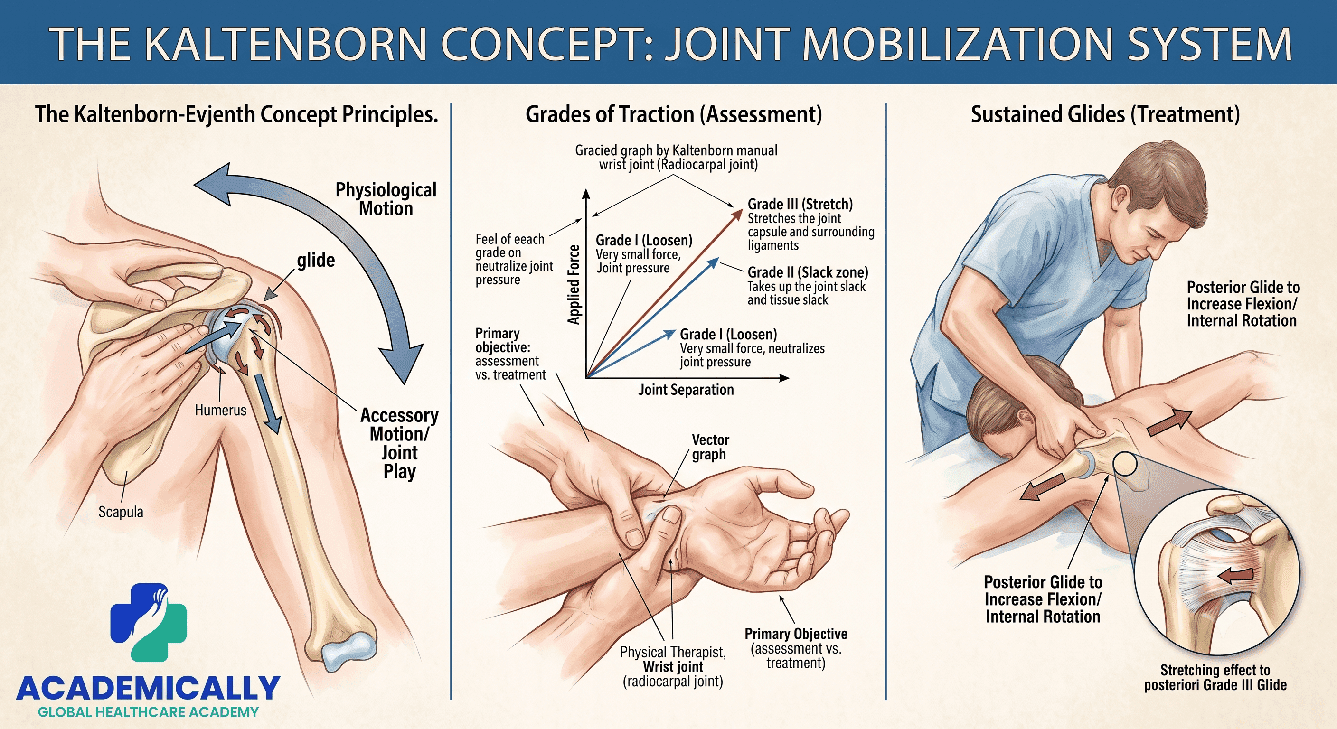
While Maitland focuses on rhythmic oscillations, Freddy Kaltenborn's approach utilizes sustained holds (glides and tractions) to stretch joint capsules over time.
- Grade I (Loosen): Neutralizes joint pressure without physically separating the joint surfaces.
- Grade II (Tighten or Take Up Slack): Separates articulating surfaces to eliminate play in the joint capsule.
- Grade III (Stretch): Actively stretches the soft tissue surrounding the joint to increase mobility
Clinical Application: Joint mobilisation is heavily utilized for conditions such as adhesive capsulitis (frozen shoulder), osteoarthritis stiffness, facet joint dysfunctions in the cervical and lumbar spine, and post-surgical joint stiffness (like post-ACL reconstruction).
Joint Manipulation
While mobilisation is slow and entirely controllable by the patient, Joint Manipulation involves a High-Velocity, Low-Amplitude (HVLA) thrust. It is performed so quickly that the patient cannot actively prevent the movement once it begins.
The Science of the "Pop" (Cavitation)
Manipulation often but not always results in an audible "pop" or "crack," clinically referred to as cavitation.
What actually causes this sound?
The synovial fluid inside our joints contains dissolved gasses (primarily carbon dioxide, nitrogen, and oxygen). When a joint is manipulated, the capsule is stretched rapidly, creating a vacuum and decreasing the pressure inside the joint. This sudden pressure drop causes the dissolved gasses to form a bubble rapidly and collapse creating the distinct popping sound.
The clinical benefits of manipulation are largely neurophysiological rather than strictly mechanical:
- Immediate Pain Modulation: The rapid thrust forcefully stimulates mechanoreceptors, which travel faster than pain signals, effectively blocking nociceptive pathways at the dorsal horn of the spinal cord (The Gate Control Theory).
- Muscle Relaxation: The rapid stretch reflex causes a reflex inhibition of hypertonic (tight, spasming) muscles surrounding the joint, creating an immediate window of relaxed mobility.
- Psychological Effect: The audible pop often provides a strong placebo and psychological reassurance of a "release" for the patient.
Safety, Red Flags, and Contraindications
Manipulation requires rigorous, flawless clinical reasoning. Because of the velocity and force involved, applying an HVLA thrust inappropriately can cause severe harm.
Absolute Contraindications include:
- Bone Pathologies: Severe osteoporosis, active osteomyelitis, bone tumors, or metabolic bone disease.
- Structural Instability: Unhealed fractures, hypermobility syndromes (like Ehlers-Danlos), or Rheumatoid Arthritis affecting the transverse ligament in the upper cervical spine.
- Vascular Conditions: Vertebrobasilar insufficiency (VBI), history of stroke, or aortic aneurysms.
- Neurological Deficits: Signs indicating spinal cord compression, such as Cauda Equina Syndrome (saddle anesthesia, bowel/bladder incontinence).
Myofascial Release (MFR) & Soft Tissue Mobilisation
Joints do not move in isolation; they are controlled by muscles, which are entirely encased in a continuous, uninterrupted web of connective tissue called fascia.
Understanding the Fascial Web
Fascia surrounds every single muscle, bone, nerve, artery, and vein in the human body. Physical trauma, poor postural habits, chronic inflammation, or surgical procedures can cause this fascia to bind down, thicken, and lose its natural pliability. These fascial restrictions can place enormous tensile pressure on pain-sensitive structures, often referring pain to completely different areas of the body along specific "anatomy trains" or fascial lines.
How Myofascial Release Works
Myofascial Release (MFR) is a specialized soft tissue therapy designed to release shortness and tightness in this connective tissue. Unlike traditional effleurage massage, which rubs over the skin, MFR engages the fascial barrier directly and waits for a physiological tissue release.
- Direct MFR: The physiotherapist physically stretches the restricted fascia by applying deep, sustained pressure using knuckles, elbows, or specialized tools directly into the restriction.
- Instrument-Assisted Soft Tissue Mobilization (IASTM): Therapies like the Graston Technique use ergonomically designed metal or plastic instruments to detect and treat fascial adhesions and micro-traumas, stimulating a local inflammatory response that promotes connective tissue remodeling.
- Indirect MFR: A much gentler approach where the therapist applies a light stretch to the fascia and holds it (sometimes for 3-5 minutes), allowing the tissue to naturally "unwind" and release on its own through autonomic nervous system regulation.
Clinical Application: MFR is highly effective for treating chronic tension headaches, fibromyalgia, plantar fasciitis, Iliotibial (IT) band syndrome, and releasing active myofascial trigger points (painful muscle knots).
In my clinical experience, and particularly after attending a comprehensive workshop focused solely on advanced MFR techniques, I have found that engaging the tissue with precise depth and waiting patiently for the release often provides the 'missing piece' for chronic pain patients who haven't responded to traditional joint work."
Comparison of Techniques
To clarify exactly when a physiotherapist uses which technique, here is a breakdown:
| Feature | Joint Mobilisation | Joint Manipulation (HVLA) | Myofascial Release (MFR) |
| Target Tissue | Joint capsule, ligaments, synovial fluid | Joint capsule, neurophysiological pathways | Muscles, fascia, connective tissue web |
| Speed / Force | Slow, oscillatory or sustained, patient can resist | High-Velocity, Low-Amplitude (HVLA), patient cannot resist | Slow, sustained deep pressure or gentle traction |
| Primary Goal | Restore arthrokinematics, stretch capsule, reduce pain | Rapid pain relief, break joint adhesions, reset muscle tone | Restore tissue pliability, release active trigger points |
| Cavitation ("Pop") | Rare | Common / Expected | None |
| Risk Level | Low to Moderate | High (Requires rigorous red-flag screening) | Low |
Global Licensing Exams And Why Manual Therapy Mastery is Mandatory
If you are an internationally educated physiotherapist looking to migrate and practice abroad, understanding manual therapy is not just about clinical excellence it is a strict, non-negotiable requirement for passing your licensing exams.
Regulatory bodies in Tier-1 countries prioritize patient safety, risk management, and clinical reasoning above all else. Because manual therapy involves applying physical force to a patient, examiners use these techniques to test your safety boundaries aggressively.
Here is how manual therapy knowledge applies to the three major global licensing pathways and how you can prepare.
Australia: The APEP Pathway (Australian Physiotherapy Equivalency Pathway)
To practice in Australia, overseas candidates must navigate the APEP (which replaced the older APC Standard Assessment Pathway).The APEP evaluates your clinical reasoning, evidence-based decision-making, and safe patient management across a Written Assessment and a highly rigorous Capability Assessment (which includes short and long clinical cases assessed by Australian examiners).
- How it's tested: The Australian physiotherapy model is globally renowned for its heavy reliance on the Maitland concept. During the APEP Written Assessment, you will face MCQs requiring you to choose the exact grade of mobilization for a specific patient presentation.
- In the Capability Assessment, you will be expected to demonstrate your clinical reasoning verbally, explicitly state contraindications, and explain how you would grade and reassess a manual therapy intervention safely. Failing to screen for Vertebrobasilar Insufficiency (VBI) before suggesting a cervical manipulation is an instant failure for safety.
Take the Next Step for Australia:
Struggling to structure your clinical reasoning the way Australian examiners expect? Most candidates fail because they lack an exam-ready structure, not because they lack clinical knowledge but guidance.
North America: NPTE (USA) and PCE (Canada)
The National Physical Therapy Examination (NPTE) in the US and the Physiotherapy Competency Exam (PCE) in Canada rely heavily on multiple-choice questions that test your decision-making.
- The Focus: You will frequently encounter case studies asking you to choose between mobilization and manipulation. You must know exactly when to use a Grade II oscillation (for an acute, highly irritable joint) versus a Grade IV mobilization (for a chronic, stiff joint).
- Understanding the bio-mechanical rules such as the Convex-Concave Rule is mandatory for answering arthrokinematic questions.
United Kingdom: HCPC Registration
The Health and Care Professions Council (HCPC) governs physiotherapy registration in the UK. The process begins with a rigorous, paper-based scrutiny of your university curriculum and clinical placement hours.
- How it's tested: The UK healthcare system heavily integrates manual therapy with active rehabilitation. If your university transcripts lack sufficient, explicitly documented hours in musculoskeletal manual therapy, your HCPC application may be flagged. You may be required to undergo a period of adaptation or take an aptitude test. You must prove your competency in joint mobilizations and clinical reasoning to meet the HCPC’s Standards of Proficiency.
Dubai: DHA Physiotherapist Exam
The Dubai Health Authority (DHA) requires physiotherapists to pass a Prometric-style computer-based exam to practice in the Emirate.
- How it's tested: The DHA exam tests a broad spectrum of clinical knowledge, but heavily emphasizes direct-access patient safety. You will face scenario-based questions where a patient presents with back or neck pain, and you must accurately identify whether manual therapy is indicated, or if the patient requires an immediate medical referral (e.g., identifying red flags like cauda equina syndrome or metastatic tumors).
Conclusion
Manual therapy remains a cornerstone of effective, evidence-based physiotherapy. Joint mobilization provides a controlled, graded approach to restoring arthrokinematic movement; manipulation offers a rapid neurophysiological reset for pain and stiffness; and myofascial release ensures the connective tissue web functions flawlessly.
For working clinicians, mastering the interplay between these three techniques allows for the holistic treatment of complex, multi-layered pain presentations. For internationally trained physiotherapists, a deep, theoretical, and practical understanding of these concepts is the key to conquering global licensing exams like the APEP, HCPC, and DHA, enabling you to build a successful, safe, and highly effective career anywhere in the world.
The journey to international registration can be complex, but you don't have to navigate it alone. Academically Global provides expert guidance, comprehensive exam preparation, and end-to-end documentation support to help you achieve your career goals abroad.